
A Practical Guide to Chronic Ankle Instability
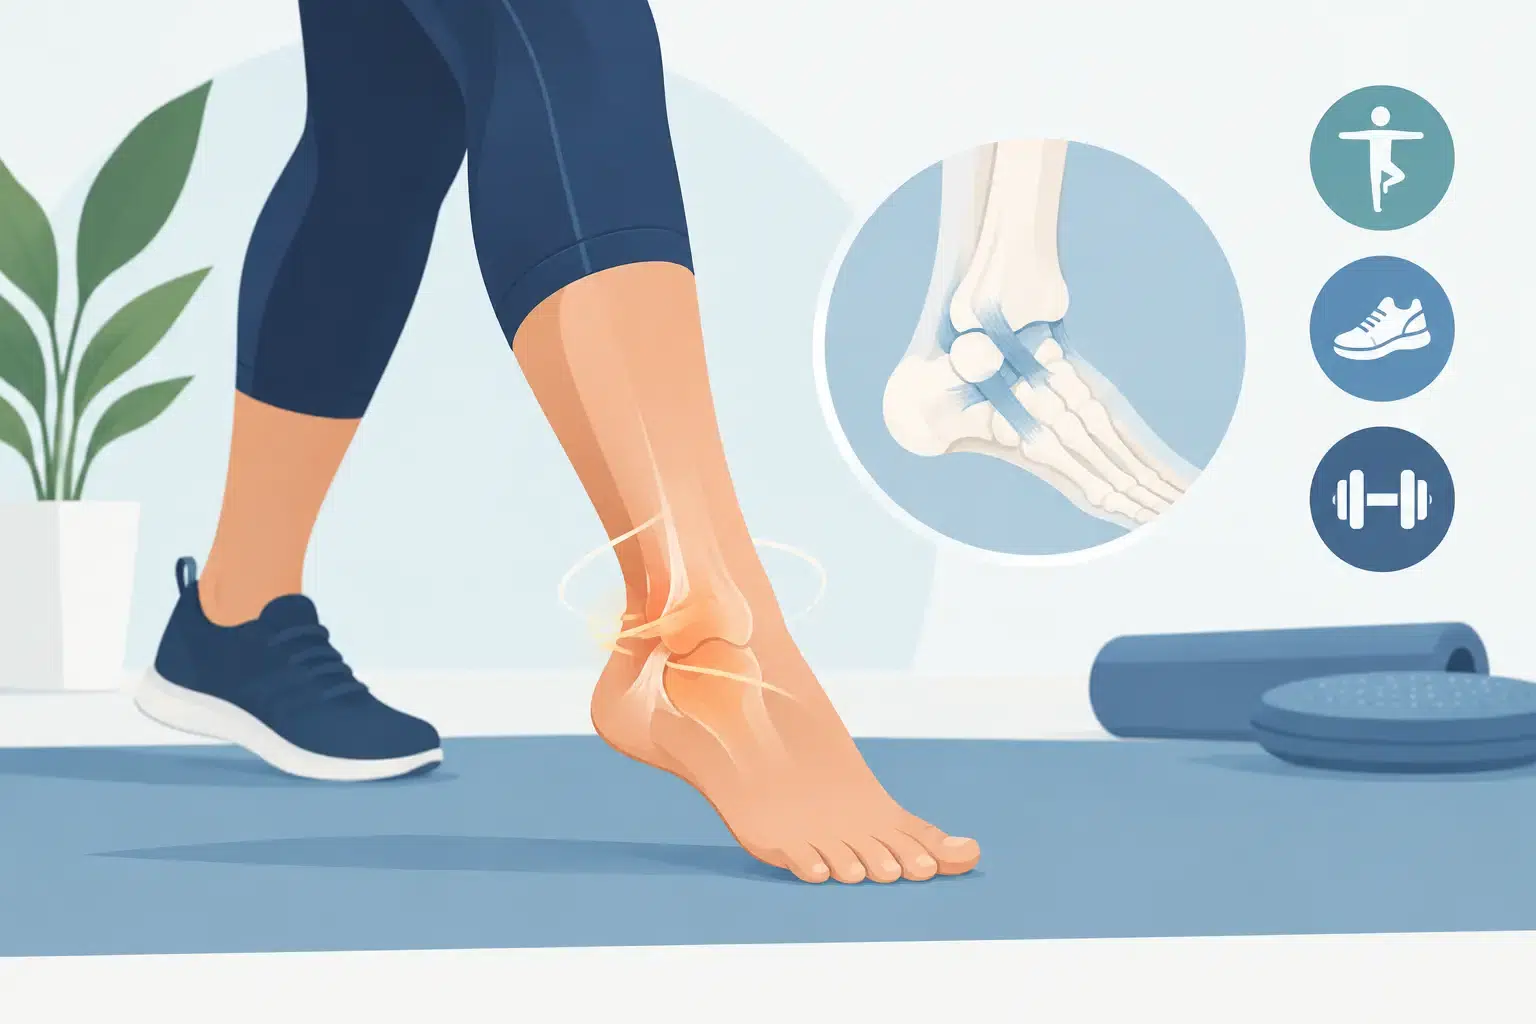
That familiar ankle roll is rarely just bad luck. If your ankle repeatedly gives way on uneven ground, during a cut on the court, stepping off a curb, or even while walking through the yard, the issue may be more than a sprain that never fully healed. It is often a movement and control problem that deserves a clear plan.
This guide to chronic ankle instability explains what keeps the cycle going, how a thorough evaluation identifies the real limiting factors, and what effective rehabilitation should prepare you to do. The goal is not simply to avoid another sprain. It is to move, train, and play with confidence again.
What Chronic Ankle Instability Actually Means
Chronic ankle instability is the tendency for an ankle to feel unreliable after one or more sprains. You may notice repeated rolling, a sense that the joint is loose, lingering pain or swelling, weakness when pushing off, or hesitation during quick changes of direction. Some people stop trusting the ankle long before they stop feeling pain.
A lateral ankle sprain, usually involving the ligaments on the outside of the ankle, is the most common starting point. Those ligaments can heal, yet the ankle may still lack the strength, position awareness, mobility, and timing required for real-life movement. That distinction matters. A healed ligament does not automatically equal a prepared ankle.
For an active adult, chronic ankle instability can show up during a round of golf, a beach walk, a run over uneven pavement, or a strength workout. For an athlete, it can limit deceleration, jumping, cutting, and confidence under fatigue. Recurrent instability may also shift stress upward into the knee, hip, and low back as your body finds ways to protect the ankle.
Why an Ankle Keeps Giving Way
The simplest explanation is often incomplete. A brace may help during activity, and rest can settle symptoms, but neither necessarily corrects why the ankle keeps failing when demand rises.
Ligament injury is only part of the picture
After a sprain, the outer ankle ligaments may remain mechanically lax. In some cases, that looseness is significant and may require imaging or consultation with an orthopedic provider. But many people with repeat sprains are dealing with functional instability: the ankle does not respond quickly or strongly enough to unexpected movement, even when the joint is not severely loose.
The peroneal muscles along the outside of the lower leg play a major role in resisting an inward roll. If they are weak, slow to activate, or poorly coordinated, the ankle has less protection in the split second that matters most.
Lost motion changes the way you load the foot
An ankle that cannot move well forward over the foot, called dorsiflexion, can make squatting, landing, running, and stair descent less efficient. Your heel may lift early, your foot may turn out, or your knee may collapse inward to compensate. Limited big-toe motion, midfoot stiffness, calf tightness, and prior foot injuries can contribute as well.
More motion is not always the answer. Some ankles need mobility; others need control within the mobility they already have. This is why a generic stretch-and-band routine often produces incomplete results.
Balance is not just standing on one foot
Your nervous system needs to know where the ankle is and how quickly to correct when the ground is unpredictable. This position awareness can be disrupted after a sprain. Single-leg balance is a useful starting point, but it is not the finish line for someone who runs, plays tennis, lifts heavy, or participates in field sports.
A capable ankle needs to manage force while the rest of the body moves. That includes controlling the trunk and pelvis, loading the hip, decelerating the knee, and using the foot as a stable but adaptable base.
Returning to activity too soon keeps the cycle alive
Pain often improves before capacity returns. That can lead someone back to sport or training while strength, endurance, reaction time, and landing control are still below what the activity demands. Each small roll reinforces the problem and may create more stiffness, apprehension, and compensation.
How a Proper Chronic Ankle Instability Assessment Works
A meaningful assessment should do more than identify tenderness around the ankle. It should connect your injury history, symptoms, movement restrictions, training demands, and goals.
A physical therapist may assess swelling, joint mobility, ligament integrity, calf and foot strength, balance, gait, squat mechanics, and single-leg control. If you are an athlete, the evaluation should also consider how you land, cut, accelerate, decelerate, and fatigue. A runner may need a different progression than a tennis player, and a golfer may need a different plan than a youth soccer athlete.
The question is not only, “What hurts?” It is also, “What fails when you ask the body to do the thing that matters to you?” That approach helps distinguish a local ankle problem from a broader movement strategy that is exposing the ankle to repeated stress.
At Back In Motion Physical Therapy & Performance, this rehab-to-performance thinking is central to The Gray Method™: identify the relevant movement limitation, address it directly, then progressively build capacity for the demands ahead.
Rebuilding an Ankle That Can Handle Real Life
Effective rehabilitation is progressive. Early work may focus on calming symptoms, restoring comfortable motion, and gradually loading the ankle. Later work should look far more like the activities you want to return to.
Restore the motion you need
If testing shows a restriction, treatment may include hands-on techniques, targeted mobility drills, and specific loading strategies for the calf, ankle, foot, or big toe. The objective is useful motion, not forcing range through sharp pain or aggressively stretching an irritated joint.
Build strength from the foot to the hip
An ankle needs more than elastic-band exercises. Those exercises can be appropriate early on, but durable progress usually includes calf raises, controlled single-leg work, foot-strength exercises, and hip strength that supports alignment during loading.
Strength should be measurable and progressive. Can you perform controlled single-leg calf raises through full range? Can you maintain foot position during a split squat? Can you step down without the ankle collapsing or the knee drifting? The answers create a more useful picture than pain alone.
Train balance, reaction, and deceleration
Balance training begins with control and advances toward perturbations, reaches, unstable or variable surfaces when appropriate, and task-specific movement. The right challenge depends on your baseline and goals. Standing on a foam pad may be useful, but it does not replace learning to absorb a landing, brake before a direction change, or regain control after an unexpected shift.
For athletes and active adults, rehab should eventually include hopping, landing, lateral movement, cutting, and speed progressions when clinically appropriate. These are not “advanced extras.” They are the bridge between feeling better in the clinic and trusting your ankle in sport.
Progress load instead of testing luck
A return to running, court sports, or high-intensity training should follow an organized progression. Start with the movement demands you can control, then increase volume, speed, range, unpredictability, and fatigue exposure over time. If symptoms rise sharply, swelling returns, or the ankle repeatedly gives way, the workload may be ahead of current capacity.
A brace or taping can be a useful temporary tool, especially during return to sport or on uneven terrain. The trade-off is that external support should complement training, not become the only thing holding your confidence together.
When You Need a Medical Evaluation
Not every unstable ankle is appropriate for self-management. Seek prompt evaluation after a new injury if you cannot bear weight, have marked deformity, severe swelling, numbness, worsening pain, or pain directly over the bones of the ankle or foot.
For ongoing problems, an assessment is warranted when repeated sprains continue despite rest, pain persists for weeks, the ankle catches or locks, swelling repeatedly returns, or you cannot regain strength and confidence with basic exercise. These symptoms can sometimes point to issues beyond a routine sprain, such as cartilage injury, tendon involvement, fracture, or substantial ligament damage.
The Standard for Returning With Confidence
The best test of ankle recovery is not whether you can get through a day without pain. It is whether your ankle can tolerate the specific demands that matter to you, repeatedly and without hesitation. That standard may mean walking Fort Myers trails, lifting without compensating, finishing a run, or cutting hard in the final minutes of a game.
Do not accept recurring ankle rolls as part of being active. With a precise assessment and a progression that builds mobility, strength, control, and sport-specific capacity, your ankle can become a reliable platform for the life and performance you want to keep pursuing.
About the Author: Dr. Scott Gray





 Call (239) 223-0484

